
Utah Measles Outbreak Is Slowing, But Newborns Are Still Paying The Price
Utah’s measles numbers are finally moving in the right direction. For many families, however, the outbreak is not over simply because a chart has begun to flatten.
Seven-week-old Kasey remains too young to receive the measles, mumps and rubella vaccine. Her parents, Abby Laskey and Liam Hammons, have therefore built their early months of parenthood around avoiding a virus their daughter cannot yet fight with vaccine-generated immunity.
Their caution has created a painful family divide. Kasey has not met several relatives, including great-grandparents living far from Utah and family members whose health may make waiting especially difficult. Flying, visiting crowded indoor spaces, and introducing the baby to a long line of relatives have all been postponed.
Utah’s measles outbreak has slowed dramatically.
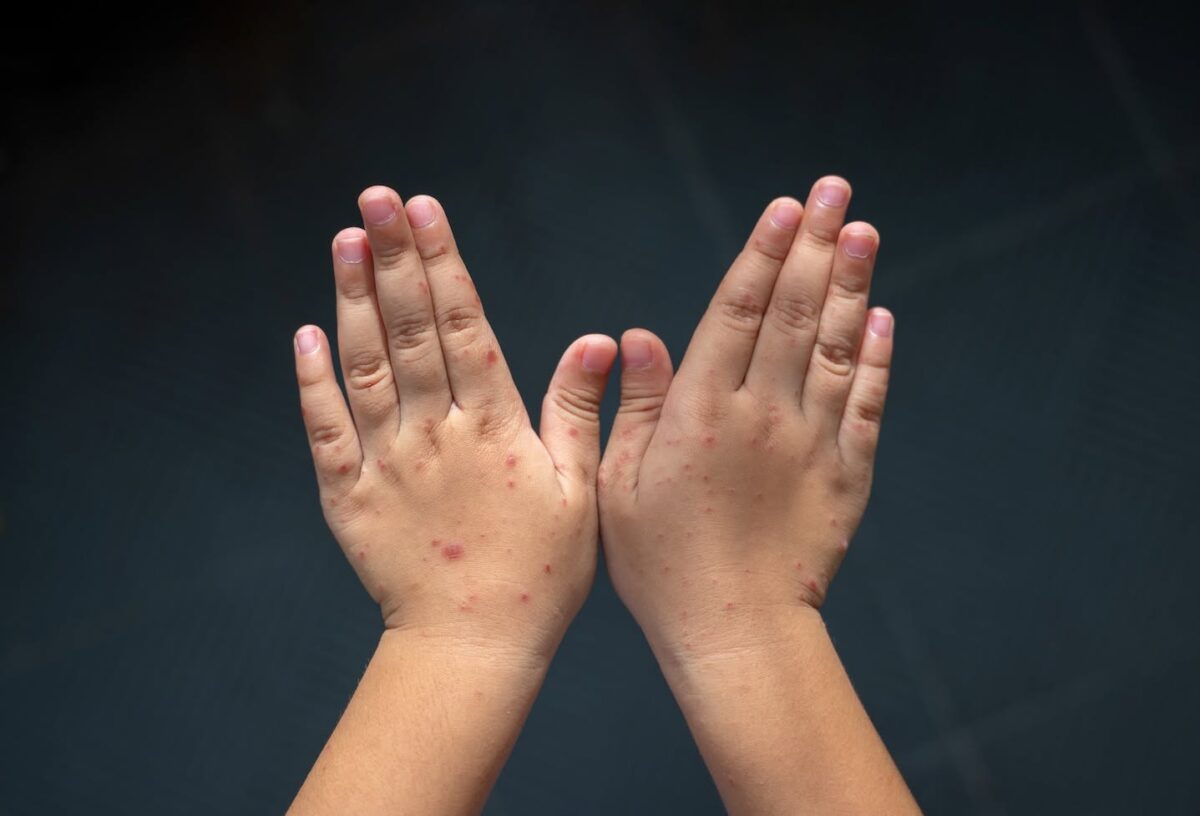
The latest Utah data provide genuine reasons for cautious optimism.
As of July 21, 2026, Utah had recorded 514 measles cases among state residents this year and 711 cases across the full outbreak period beginning in 2025. Only six Utah residents had been diagnosed during the previous three weeks, suggesting that the intense transmission seen earlier in the year had substantially weakened.
Utah health officials also reported no newly identified public exposure locations as of July 17.
Those numbers matter. They suggest that vaccination efforts, isolation, contact tracing, public warnings and changes in community behavior have helped interrupt many routes of transmission.
But we should not confuse a slowdown with eradication.
Measles can remain infectious in the air for as long as two hours after an infected person leaves a room. A susceptible person does not necessarily need to touch the patient, share a meal or have a face-to-face conversation. Simply entering a contaminated indoor space may be enough.
That makes even a small number of cases unusually disruptive. One infected traveler, customer, worshipper, student or clinic patient can trigger exposure investigations involving hundreds of people.
For vaccinated adults, this may represent a manageable risk. For a seven-week-old infant, it can determine whether the family boards an airplane, enters a museum or visits an elderly relative.
A seven-week-old baby has no MMR option.
The routine childhood vaccination schedule recommends the first MMR dose between 12 and 15 months of age. The second dose is normally given between ages four and six, although it may be administered earlier when medically appropriate and sufficiently separated from the first dose.
During outbreaks or before international travel, health authorities may recommend an additional early dose for infants between six and 11 months old.
That early dose offers another layer of protection, but it does not replace the standard childhood series. A baby vaccinated before the first birthday must still receive two routine doses later.
Kasey is not six months old. She is not close.
At seven weeks, there is no early MMR dose available to her. Her protection depends almost entirely on avoiding infected people and being surrounded by individuals who are already immune.
Utah now considers the risk of contracting measles relatively low and has returned to standard early-vaccination guidance. State health officials say an additional dose remains allowable for infants six months and older. Still, it is not generally encouraged in places without active spread unless the child will travel internationally.
That policy may be reasonable at the population level. It does not erase the uncertainty confronting individual parents.
A virus does not need to be spreading everywhere to reach one airport, one waiting room or one family gathering.
The national measles outbreak is still growing.
Utah’s improvement stands in sharp contrast to the national picture.
A Johns Hopkins University tally had recorded 2,295 U.S. measles cases by July 22, already exceeding its total for all of 2025. That makes 2026 the country’s worst measles year in 35 years, with more than five months remaining.
The Centers for Disease Control and Prevention reported 2,260 confirmed cases through July 16. Its total was slightly lower because the CDC receives direct submissions from jurisdictions and updates on a different timetable, while Johns Hopkins aggregates publicly available state and local figures.
The CDC data also reveal who is carrying the greatest burden:
- Half of confirmed cases involved people between five and 19 years old.
- Another 20% involved children younger than five.
- Approximately 93% of patients were unvaccinated or had an unknown vaccination status.
- At least 146 patients had been hospitalized.
- Roughly 93% of confirmed cases were associated with outbreaks.
We are therefore not looking at scattered travel-related infections that were quickly contained. We are seeing sustained clusters in communities where the virus has repeatedly found enough susceptible people to continue moving.
That national transmission is what keeps Utah parents cautious even when Utah’s weekly numbers improve.
An airplane does not carry only Utah residents. A wedding guest may arrive from another state. A relative may pass through multiple airports. A visitor may be contagious before the characteristic rash appears.
Local statistics can describe local transmission. They cannot place a protective border around an infant.
Why falling vaccination coverage affects babies first
The MMR vaccine provides strong individual protection. One dose is about 93% effective against measles, while two doses are about 97% effective.
Newborns cannot benefit from those percentages yet.
They rely on community immunity, meaning the virus encounters so many immune people that it struggles to reach those who cannot be vaccinated or may not respond adequately to vaccination.
Maintaining that protection requires consistently high coverage because measles is extraordinarily contagious. Up to nine out of 10 susceptible people who have close contact with an infected individual may become infected.
The World Health Organization recommends at least 95% coverage with both measles vaccine doses in every community seeking to eliminate transmission. National averages are not enough when undervaccinated residents are concentrated in particular schools, neighborhoods, or religious and social networks.
The United States has moved in the opposite direction.
MMR coverage among kindergarten students fell from 95.2% during the 2019–2020 school year to 92.5% during 2024–2025. The CDC estimated that approximately 286,000 kindergartners attended school without documentation showing they had completed the required MMR series.
A decline of 2.7 percentage points may look modest on paper. Across millions of children, it creates large pockets of susceptibility.
The cost of reduced vaccination does not remain with the people who decline or delay a dose. It moves outward.
It reaches the infant who cannot be vaccinated, the cancer patient receiving immune-suppressing treatment, the pregnant woman without immunity, and the family forced to cancel a final visit with an aging relative.
“We all had measles” overlooks the children who suffered.
Some older Americans remember measles as an unavoidable childhood illness. That memory is understandable because widespread infection was once common.
Before the vaccine became available in 1963, an estimated three million to four million Americans contracted measles during an average year. Many cases were never formally reported. Hundreds of thousands were documented, approximately 48,000 patients were hospitalized annually, and hundreds died.
Many survivors recovered without permanent injury. Others developed pneumonia, brain inflammation, deafness, cognitive disability, or fatal complications.
The fact that millions of children once experienced a disease does not prove that the disease was harmless. It shows how little protection existed.
We would not describe an infectious illness as mild simply because suffering was widespread enough to appear normal.
Vaccination changed what Americans considered normal. It allowed parents to stop treating childhood infection as an unavoidable rite of passage. It also made the consequences less visible, creating room for later generations to underestimate what had disappeared.
Measles can weaken protection against other diseases.
The virus can also damage immune memory.
Our immune systems build libraries of information after infections and vaccinations. Memory cells help the body recognize previously encountered threats and respond more quickly when they return.
Measles infects and destroys some of those cells. Research has found that children may lose a substantial portion of the antibodies that previously protected them against unrelated pathogens. This phenomenon is commonly described as immune amnesia.
Separate research has supported an association between measles infection and increased vulnerability to other infectious diseases. Scientists studying long-term population patterns have estimated that the effect may remain detectable for approximately two to three years.
That means the burden of measles cannot be measured only by counting fever cases, hospital admissions or deaths recorded during the acute outbreak.
A child may survive the immediate infection and then face a weakened ability to fight other illnesses months or years later.
Vaccination prevents that chain by preventing measles infection in the first place.
The United States has not formally lost elimination status yet.
The resurgence has raised another major question: whether the United States will lose its measles-elimination designation.
The country was declared free of continuous endemic measles transmission in 2000. Elimination did not mean the virus had vanished permanently. Imported infections could still occur, but public health systems were expected to prevent them from producing uninterrupted domestic transmission lasting at least 12 months.
The Pan American Health Organization is scheduled to review the elimination status of the United States and Mexico in November 2026.
For the United States, the assessment period begins with the January 20, 2025 onset of the outbreak under investigation. Reviewers will consider epidemiological evidence, whole-genome sequencing, and whether the same viral lineage circulated continuously for at least one year within a defined geographic area.
The outcome has not been formally decided.
That distinction matters. The evidence may place the designation in serious jeopardy, but the responsible conclusion is that U.S. elimination status remains under review rather than already officially revoked.
The designation is more than a symbolic public health trophy. Losing it would show that the country had allowed a vaccine-preventable virus to reestablish sustained transmission after keeping it eliminated for more than two decades.





